Guest viewing is limited

Minimally Invasive TKR

Status
Not open for further replies.
I don't see what the big deal is anyway? I had a quad cut. Walked out of the Hospital. At home going up and down stairs on day 5. 5 weeks post op I am exercising and walking without any pain killers. Planning on going back to work next week, today spending most of the day sitting or upright. Even cleaned up the kitchen and made the kids lunches for school tonight. I think really this is an individual experience which will take longer or shorter depending on attitude, health, and patience. In six months to a year we shall all be better off for the experience if things go well. I chose my surgeon due to the excellent work he does and the great St. George Hospital in Sydney. It was like a health retreat for the unhealthy and I thrived in my immediate recovery. I have had a few hiccups along the way, but really right on target for what state I wanted to be in week 5 post op. Once you chose your surgeon, just trust that you will get the best result he/she can deliver. I wanted MIS/Quad sparing technique, but was not a candidate, it really has not slowed me up in comparison to all the MIS people posting. There are so many other factors, but still the more in your favor the better.
Ask the questions: Quad sparring/MIS, them chose the surgeon you believe will give you the best outcome.
 
It was like a health retreat for the unhealthy and I thrived in my immediate recovery.
You, AussieBill, missed your calling not being in advertising. The "health retreat for the unhealthy" is a great description!

Glad you are doing so well. If I remember correctly, you have a job that is more physically demanding so you must be feeling pretty good to be returning to work.
 
AussieBill, in terms of long term outcome, it isn't a big deal as long as you have an excellent, experienced surgeon. If I'm a good candidate for it, I want to make sure I chose a surgeon that does do it, because since I'm having Bilateral TKR, and will have no "good" leg to go to, the short term recovery matters more. The point here is that if someone is told over and over that all surgeons do quad sparing so don't worry about it, they may not ask and assume that their surgeon does not do the quad snip. They may have wanted to make the choice if they had known there was a choice to make. Josephine, God bless her, is an amazingly knowledgable, resourceful and helpful person, but on this point she had been unintentionally giving some inacurate advice, and doesn't want to address or correct this in a helpful manner.
 
Great info on all fronts, love the dialogue and tangents, keeps the brain firing. this Friday I'm going in for essentially a 3rd opinion. Actually, it's with the OS I want to do the procedure after much research. But alas, need to hear is diagnosis also. Anyone have experience(good or bad obviously) with Radiosteriometric Analysis...My OS is a leading proponent of this......
 
Great info on all fronts, love the dialogue and tangents, keeps the brain firing. this Friday I'm going in for essentially a 3rd opinion. Actually, it's with the OS I want to do the procedure after much research. But alas, need to hear is diagnosis also. Anyone have experience(good or bad obviously) with Radiosteriometric Analysis...My OS is a leading proponent of this......

I haven't heard of this. I'll tag @Josephine:
 
Never heard of it either but snitched this info from the HSS site. Very interesting .....

RSA is a powerful research technique that is currently being studied at Hospital for Special Surgery (HSS) for joint replacement patients. RSA stands for radiostereometric analysis, which describes a special way of taking two x-rays from different directions at the same time, creating a “stereo” image. RSA x-rays allow surgeons to measure precisely how the body and the implant are interacting. This enables them to accomplish two goals at once – while measuring the patient’s progress, they can also use information from this research to improve implant design and technology for future patients.
 
In hindsight perhaps I would have done more research. I only saw two surgeons and the second I felt was more up to date, yet he used out of date techniques (quad cut) and up to date techniques? I had a pain catheter inserted in the site which fed meds directly to the traumatized tissues. I had virtually no pain in the knee on day one and day two post op. It was removed 24 hrs post op. This was significant in getting up and walking, showering, using the loo. I was walking up and down the halls with just crutches on day two. I missed out on MIS due to wide bones, skinny legs: My surgeon does this technique, but thought the traditional method was better in my case. How common is the pain catheter ? and is this also an old technique I wonder now: in any case it did the trick.

Hi 1Elisea, Going back to a desk job: computer graphics (with some work which does requires standing for short bursts). Last night first night with no pain meds and slept the same pattern waking up every 3 or 4 hours.

Hi Janet, I was just making the point that a Quad cut is only one factor: If my surgeon did a better job with the tools and techniques he uses regularly and built me a knee which is straight and bends well then I would rather he have the extra work space. If I insisted he not cut the Quad and I got a joint that didn't work as well then that would be a high price to pay. I do get if given the choice and the final result is just as good then go with the non Quad cut. It just has not slowed me down. I have more issues with scar tissue below the kneecap, than muscle. Taking it slow is really the best advice post op. It will all come with time.
 
HSS looks like THE hospital to use by what I have read on this forum. Not a reality living Down Under.

I had to have a 4 foot x-ray done from the torso to my feet pre-op and post-op to check alignment and fit. Only a few places available in Sydney for this.
 
B4000,
Good luck with your choices. The RSA sounds like another good tool. It seems like your very informed about this and I am sure your outcome will be great.
 
AussieBill, The point you were making is absolutely right. I was also told that it is very difficult to do on some men with very muscular legs. We were making different points, that's all. :thumb:
 
No worries Janet,
I think the more things going for you in speed of recovery the better. I agree if one can have MIS and no Quad snip the better. Qustions should be asked and better to be clear on what is to happen in theater.
 
All...super stuff here. I have been working with my OS for over a year and it has finally come down to TKR. I am terrified. I have liked my OS, but on my last visit I started asking questions like...do you perform MIS? The answer...that is just a marketing ploy. The next question (I am 5') is there a replacement that will fit me appropriately? That was met with a chuckle/laugh. My surgery is June 1 and I amhaving second thoughts about this guy.
 
I am happy to hear that---any OS who would laugh at my questions is not the kind of guy I would want to work with.

Why can't he just give you the info instead of humiliating you with his laugh--as though that were a stupid question.

I had an OS that everyone in town told me had great results with his tkas--but I would not use him for exactly this reason. he told me to let him worry about the implant and how surgery would go. He also did not want to answer questions---what an absurd way to behave. I expected him to call me "the little woman".

I saw one OS who actually called me "HONey" I got up and walked out of his office. Who do these men think they are?

My fake knees seem huge--if I were small I would really need an answer to what is a perfectly acceptable question.

I found a knee specialist who spent two hours with me not he first visit answering questions. he is not warm and fuzzy, but at least he respects me.
Kelly
 
I got good references on an OS for his surgical technique from a few pts that I met through my work. A few had mentioned that his bedside manner was so-so, but they did not care because they wanted the good surgeon.
I looked into him, (ratings on Vitals, etc.) and met a few more pts who had surg. with him. Several had mentioned that he was demeaning, and downright nasty, but a good OS. When I checked further, I saw that he seemed to have a new partner every few years. Hmmm...
So I never went to him because I wanted a good relationship with my OS, where I could ask questions at any time, and feel that someone would get back to me.
In the end I got Prince Charming (I LOVE my OS), but really- who wants a relationship like skigirl mentioned (calling me 'honey', not answering legitimate questions- ugh) with their OS?
I think implant size is a very valid question. I am 5'2', kind of smallish-boned and wondered the same thing. When I consulted with my beloved OS, he discussed the pt-specific cutting blocks for me and so I knew the size issue was no longer a concern for me.
If someone is putting their hands inside my body, and changing my body- I want a good relationship with them!!
I would walk out if someone laughed at me!
You should find a different OS, IMO!
 
I think there may be some confusion on the terms as they are being used. I'll get back to this in a moment.

Most surgeons have adopted some form of the techniques of MIS TKA into their surgery. The instruments and guides are better and smaller than in years past. Overall, the incisions are smaller than they were 10 years ago. However, the marketing of MIS created a need to make the incisions smaller and smaller. In some circumstances this has actually lead to malpositioning of the knee components. Studies have shown slightly quicker recovery times with true MIS, but sometimes at the expense of the final outcome.

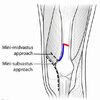
As for the terms used in the exposure in knee replacements, take a look at the diagram I have attached. The midvastus and subvastus approach are labeled. These approaches were created as part of the original descriptions of MIS techniques. The blue line is the more traditional approach into the quad tendon, which is still used by a large proportion of surgeons. The red line is the "quad snip." The addition of a quad snip is rarely used as an approach for a primary TKA, but still has its place in the role of revision TKA.

[Bonesmart.org] Minimally Invasive TKR

Orthodoc
 
Great post, orthodoc! Thanks!!! I'm going to clip it to our thread in the BoneSmart Library.
 
Orthodoc, that diagram is really helpful. I think we've been talking apples and oranges here. There would be a difference in extending the blue line into the quad muscle to make a bigger opening, vs. cutting it across to make a sort of flap opening. It was never explained quite like that. Thanks!
 
Yes, I have never seen that diagram before. Very useful info.

So, my surgeon uses a mid vastus approach---but he also uses computer positioning for the knee. I can see why now. Kelly
 
Orthodoc,

Thank you for that information. My Surgeon said he cut the Quad Muscle right down the middle, which I thought was a Quad SNIP and in fact it seems it is a normal part of the process in TKR surgery. My progress has been very good. Better ROM now than in theater, Going OK without Pain Meds, Getting ready to return to work next week. All positive from this end.
 
Status
Not open for further replies.
Back
Top Bottom