

You are using an out of date browser. It may not display this or other websites correctly.
You should upgrade or use an alternative browser.
You should upgrade or use an alternative browser.
Bilateral THR A thank-you and an introduction
- Thread starter NewlyHip
- Start date
- Status
- Not open for further replies.


@NewlyHip , just catching up with your amazing progress. Well done! I see no one has given you your official recovery articles to refer back to. I'll do it now - if only to keep you from doing things like mowing your lawn so early out!  Slow and steady - remember is a marathon, not a sprint.
Pain management and the pain chart
Healing: how long does it take?
Chart representation of THR recovery
Dislocation risk and 90 degree rule
Energy drain for THRs
Pain and swelling control: elevation is the key
Activity progression for THRs
Home physio (PT)
Post op blues is a reality - be prepared for it
Myth busting: on getting addicted to pain meds
Slow and steady - remember is a marathon, not a sprint. Pain management and the pain chart
Healing: how long does it take?
Chart representation of THR recovery
Dislocation risk and 90 degree rule
Energy drain for THRs
Pain and swelling control: elevation is the key
Activity progression for THRs
Home physio (PT)
Post op blues is a reality - be prepared for it
Myth busting: on getting addicted to pain meds
cr8tvt
junior member
hi newly -
i can't tell you how much i admire all of your candor and courage in discussing these topics. it just makes me cringe. i was officially told today i need 2 new hips. since you are in NY, and about my age, and seem to have the same attitude (back in the gym on day 3 foolishness), i was curious: did you go to HSS? who was your surgeon? what device type did he use? did you get a 2nd (3rd) opinion? - thanks - (or are these questions not asked on the forum?) - i like the idea of just choosing a surgeon and trusting him/her, but they all seem likable and knowledgeable to me . . .
i can't tell you how much i admire all of your candor and courage in discussing these topics. it just makes me cringe. i was officially told today i need 2 new hips. since you are in NY, and about my age, and seem to have the same attitude (back in the gym on day 3 foolishness), i was curious: did you go to HSS? who was your surgeon? what device type did he use? did you get a 2nd (3rd) opinion? - thanks - (or are these questions not asked on the forum?) - i like the idea of just choosing a surgeon and trusting him/her, but they all seem likable and knowledgeable to me . . .
OP
OP

NewlyHip
member
@cr8tvt, hello and best wishes as you sort things out prior to surgery! (Please excuse this long-winded response, but I have a lot of time on my hands at the moment!)
For me personally, I spent many months in a sort of medical sleuthing environment trying to pinpoint where my various aches and pains were actually coming from. After working with a physiatrist, neurologist, and physical therapist, it was determined that my radiating pains (traveling to areas mainly in my back, hip, and leg areas) were the result of relatively severe osteoarthritis in each hip.
I am actually in the western part of New York State and had two surgeons I considered using, one who does the anterior approach and one who does the mini-posterior approach. I called the anterior-approach fellow’s office and was told it would be 9 months to surgery! With the severe pain and disability I was experiencing it was not even comprehensible to envision a 9-month wait.
The mini-posterior fellow was very highly recommended to me by my physical therapist, who said to me that, in all his years of working with this doctor’s patients, he had never seen a bad hip surgery from this fellow. My wife and I went to talk with this surgeon, and we fell in love with the guy — very down-to-earth and genuinely a nice person. He had also done many bilateral operations and was WILLING to do bilateral surgery with me. The wait would also be half of what it would be for the other surgeon!
I must say that I did a great deal of research into the posterior vs. anterior approach and came to the conclusion that there was very little actual difference between “mini-posterior” (smaller incisions and less muscle cutting) and anterior approaches, at least for me personally. And, with the mini-posterior approach, my recovery has been nothing short of remarkable. I was progressing so well that the folks in the hospital could hardly believe it. A physical therapist, after deciding I could do it, had me walk up and down a twenty-step staircase (one foot per step) from one floor to another in the hospital just two days after surgery. You can see from my little video clip how well I was doing with walking just three days after surgery. And the pain has been so minimal that my major pain issues involve some ankle arthritis that bothers me when I walk a long distance outside.
I am going to see my surgeon tomorrow to get the staples removed and am going to get some specifics on what prosthetic devices were actually used. The surgeon’s PA told me before surgery that they don’t really know for sure what they will use before they open up the surgical site and view the bone structure, etc.
Here is the best advice I can give you. Find a surgeon who comes highly recommended by anyone you trust who works in the medical field. Not only did I have a recommendation from my PT person, but the surgeon was also highly recommended by my primary care physician and the charge nurse from the hospital floor I would be staying on after surgery. Once you have a name or two or three, I would choose the surgeon that you feel most comfortable with. And then I would suggest trusting this surgeon to handle things in the most appropriate way. I deferred to my surgeon on things because I felt unqualified (and uninterested really) to be second-guessing him.
To me the surgeon is the key. Concentrate on finding this person and then just try to relax. Please keep me posted on how things are going! Good luck!

psychteach
graduate
- Joined
- Dec 26, 2013
- Messages
- 730
- Age
- 62
- Location
- Palm Beach, Florida
- Gender
- Female
- Country
 United States
cr8tvt
junior member
thanks newly and psych -
i'm almost there. the surgeon i saw at HSS seems incredibly knowledgeable and experienced. my hips are straightforward, nothing complex, one is bad and the other worse, so they need to be done and it might as well be sooner than later so i can enjoy them (if i can wait the 6-8 mos. for them to feel "normal"). how long will it be until i can mow the lawn?
he recommended a smith&nephew, metal on plastic that is the new "gold-standard". i think picking another HSS surgeon would be like flipping a coin, so i don't know what a 2nd opinion would provide (other than that i could cross that off my list) so i'll probably do it anyway. i also need to find out who would actually perform most of my surgery, e.g. does a fellow or resident do most of the initial cutting and closing? and should that make a difference to me? (btw - the guy i saw uses a mini-posterior approach, to get better access to the site and even with the anterior approach some tissue (ligaments? tendons?) sometimes still need to be cut and re-attached. he also uses some computer assisted alignment tools for accuracy and consistency in positioning the implants).
the post-op care seems daunting (don't sit in a recliner? when i'm not doing something, i live in a recliner.) and that's hard enuff doing 1 hip. my biggest concern right now is doing both hips at the same time. i'd really like to get it over with (i rip bandaids off) and get on with life (and perhaps a new knee or 2 . . . ). how long did you "not have a leg to stand on"? having done both together, are you happy with that decision? (i'm afraid that after the first one it would be difficult to go back . . . for me the anticipation is worse than the event). and your experience makes it look like the right move.
and thanks again for all the info and support. there's nothing like talking to someone who's been there.
I can't tell you how important this is. Trust in your surgeon is key. You are entering a partnership. If you trust that partner the rest will fall into place. This includes the implant. No need to research. Your surgeon will chose the implant(s) that are appropriate in your case. They will be implants that he/she has experience with - after all you wouldn't want your surgeon to be using your case as a trial would you?Once you have a name or two or three, I would choose the surgeon that you feel most comfortable with. And then I would suggest trusting this surgeon to handle things in the most appropriate way.
@cr8tvt you can indeed use a recliner during recovery. Many of our members sleep in their recliners for the first few weeks of recovery. The 90 degree restriction is really easier to deal with than you are imagining. Have a read in the hip recovery area. You'll find lots of new hippies with stories to tell.
OP
OP
NewlyHip
member
@cr8tvt:
how long will it be until i can mow the lawn?
I must say that, much to my wife's chagrin, I mowed the lawn two days ago with my garden tractor. After listening to the voices of wisdom however, on this site and elsewhere, I have changed my mind about the safety and prudence of mowing the lawn. Indeed when I was riding around on the mower I hit a small indentation and it jostled me enough that I felt quite a bit of pain and a loss of balance. The mowing could probably wait about 6 weeks in my opinion. My two daughters are back from college and have agreed to be my landscape experts for the next few weeks!
i don't know what a 2nd opinion would provide
I personally did not seek a second opinion because my wife and I were so happy with the first surgeon we met with. He came so highly recommended and was so personable and down-to-earth that I felt at peace with him and his staff from day one.
does a fellow or resident do most of the initial cutting and closing
My surgeon did not go into specifics but I am sure he did the entire procedure himself with assistance from his PA and the anesthesiologist (and his PA). If anyone other than the surgeon you choose will actually do some surgery then the surgeon has a strong ethical obligation (and quite frankly legal obligation) to inform you of who this other surgeon would be.
the guy i saw uses a mini-posterior approach
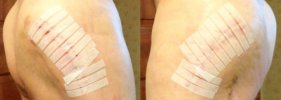
My surgeon also used the mini-posterior approach (check out my scar photos to see the incisions) and it went wonderfully well for me personally. I had so little pain afterward that I found it remarkable. I was sitting up on the side of my bed a few short hours after the surgery and was up and walking the next day.
(don't sit in a recliner? when i'm not doing something, i live in a recliner.)
My biggest issue with the 90 degree precaution is that I am 6 feet 4 inches tall. So my wife rented a hospital bed which I am now using as an oversized recliner. I also have a regular recliner but the bed is so much easier for me to use — and I think I sleep better when I doze off every now and then.
my biggest concern right now is doing both hips at the same time. i'd really like to get it over with
My personal feeling in wanting to have both hips done at once is exactly in line with your thinking. One surgery, one recovery, with both hips rid of arthritic pain. In my case both hips were so bad that, had I only had one hip repaired, I would be rehabbing with a surgically repaired hip and another hip that hurt even more than the repaired one. And everything went remarkably well having both done at once! The only thing to be aware of is that it is a more intense experience for your body to endure. In my case I needed to have some transfusion help to get my hemoglobin levels up where the surgeon felt comfortable with things.
how long did you "not have a leg to stand on"? having done both together, are you happy with that decision?
In my case there was absolutely no sense of "not having a leg to stand on" AFTER the surgery. It was BEFORE the surgery that I felt like I had no leg to stand on! The prosthetic devices can accept weight-bearing activity as soon as you feel ready to begin moving around.
If you really feel comfortable with your first surgeon, and they will do a bilateral procedure, I personally would not bother with a second opinion. The waiting to see the second surgeon could involve many weeks actually and you seem to be like me in wanting to just get the whole thing over with.
I hope I have been of some help to you in sorting all this stuff out. The whole experience getting ready for surgery can be a bit overwhelming. GOOD LUCK!
Last edited by a moderator:
cr8tvt
junior member
thanks jaycey -
i think a large part of my problem is that i'm pretty active now despite my difficulties - (for example, i mowed the lawn yesterday, push gas mower). but i'm sure the quality of life would be better with new hips. (as my brother-in-law/physician said when i told him that i can still tolerate my condition: "you could tolerate crawling . . . " - (good point . . . )
i'm leery about what i won't be able to do and for how long? e.g. - when CAN i mow again? (not that that particular activity is crucial, but it gives me an idea of real recovery time, not just ability to take some steps. when can i resume going to the gym? the booklet HSS provided mentioned doubles tennis - does that mean singles would not be recommended? (i haven't played at all for a while, but, as mentioned, i just want to set my expectations appropriately). if i have bilateral hip replacement at the end of july, will i be comfortable taking a bus tour vacation in croatia Nov. 1 (3 mos. later) that will include lots of walking. the surgeon was ok with that, but it'd be nice to have reassurance from people who have done it.
and mostly thanks for the recliner . . . . (;-))
and where can i find a list of all the things i'll need at home for recovery? i have a list from HSS, but it may not be complete (you know, with those little things) and where can i get them in the US for the best prices? is used equipment ok. or not worth the trouble of finding the right stuff and disinfecting everything?
thanks
cr8tvt
junior member
thanks newly - (i wrote the one above while you were writing yours - )
your advice and experiences have eased my mind quite a bit -
i guess i just have to think about 8-12 mos. from now and focus less on the next few -
thanks -
your advice and experiences have eased my mind quite a bit -
i guess i just have to think about 8-12 mos. from now and focus less on the next few -
thanks -
Here's a list from our Library: Recovery Aids: A comprehensive list for hospital and homewhere can i find a list of all the things i'll need at home for recovery?
@cr8tvt how about starting your own thread in the Hip Pre-op area. I am certain others contemplating this journey have the same questions and will benefit from the input you are getting here.

younghippie
senior
- Joined
- Feb 1, 2014
- Messages
- 492
- Age
- 50
- Gender
- Female
- Country
- United States
Congrats, @NewlyHip Sounds like you are doing great!  I love that you posted the video. That is wonderful for those that are still pre op to see. Very encouraging.
@cr8vt I wanted to respond to this- does a fellow or resident do most of the initial cutting and closing
I chose to have my THR done at a university research hospital where there tend to be a lot of residents about. So, that was a big concern for me. I asked my surgeon directly if a resident would be allowed to touch me in the OR. His response was very serious... he said, "I am VERY particular about that. I am the only one performing surgery on you and if a resident is present, they will not have any interaction with you in that way. I am the surgeon..." That made me feel a lot better. Also, I ended up with a small 4 inch incision that is so clean and flat that it looks like a plastic surgeon did it (internal stitches, glue, water proof bandage). I have no doubt my surgeon did that! I would just simply ask your surgeon. I also asked what the PA would be allowed to do, as they really are not qualified to do anything surgical in my opinion given their level of required training. He indicated that the PA dealt with positioning of my body, holding my leg, etc. It gave me a lot of peace to know these specifics. Best of luck!
I love that you posted the video. That is wonderful for those that are still pre op to see. Very encouraging. @cr8vt I wanted to respond to this- does a fellow or resident do most of the initial cutting and closing
I chose to have my THR done at a university research hospital where there tend to be a lot of residents about. So, that was a big concern for me. I asked my surgeon directly if a resident would be allowed to touch me in the OR. His response was very serious... he said, "I am VERY particular about that. I am the only one performing surgery on you and if a resident is present, they will not have any interaction with you in that way. I am the surgeon..." That made me feel a lot better. Also, I ended up with a small 4 inch incision that is so clean and flat that it looks like a plastic surgeon did it (internal stitches, glue, water proof bandage). I have no doubt my surgeon did that! I would just simply ask your surgeon. I also asked what the PA would be allowed to do, as they really are not qualified to do anything surgical in my opinion given their level of required training. He indicated that the PA dealt with positioning of my body, holding my leg, etc. It gave me a lot of peace to know these specifics. Best of luck!

Sue629
senior
@cr8tvt I also asked my surgeon if she does it all, and she looked at me and said "you are my patient, you are my responsibility and I don't let anyone touch you other than my PA that only holds your leg. I close you and even move you onto the bed myself" I felt so at ease and so comfortable. I had a posterior trhr on 4/30/14 and my recovery has been truly amazing. All my best...Sue

MajorHeidi
big-cheese
@NewlyHip @cr8tvt I also chose a teaching hospital and had the same concern as you and @younghippie .
I discussed this with the OS and the PA (separately) and got the same answer that the OS does all the cutting and computer positioning as it is his responsibility. They did indicate that people (residents/ med students ) might be
in the theatre observing ONLY.
The PA did say that either himself or one of the other doctors under the OS would likely do the stitching/gluing which didn't seem problematic.
On the recliner question, yes I got a nice recliner with automatic power. I also went on Amazon
and got bed risers (set of 4) to put under it and raise it up by 5 inches. That was the smartest
decision I made.
Best wishes...
psychteach
graduate
- Joined
- Dec 26, 2013
- Messages
- 730
- Age
- 62
- Location
- Palm Beach, Florida
- Gender
- Female
- Country
- United States
The good thing about a teaching hospital as I used one too.( Cleveland Clinic) is that they do not have to advertise or push for your business as I felt with other OS's. I had a fellow with my doctor in the operating room. He was already an orthopedic surgeon but was learning anterior from my surgeon! I loved him.. Such a great way about him.. Calmed me down and great bubbly personality. They both came to visit me in hospital twice a day but the fellow usually was there earlier so stopped by first.. When my surgeon came in.. I knew who wore the pants there!!! My OS showed he was in charge.. I had no worries he would be same in surgery!! Very serious about his stuff and the way it was to be done
Sent from my iPhone using BoneSmart®
Sent from my iPhone using BoneSmart®
CodeGirl
junior member
@cr8tvt , one thing to consider if you are willing to see a doctor there who does the anterior approach is that there are very few restrictions on an anterior hip replacement from day 1. There is no 90 degree restriction, no rules about crossing the midline, no requirements to sleep on your back with a pillow between your knees. These are all unnecessary with the minimally invasive anterior approach because all muscles and tendons remain intact. There is no cutting of either. I went home on the same day as my surgery as soon as I could demonstrate that I could dress myself, walk up and down stairs and use the bathroom unassisted. I needed very little pain killer because I was so numb from the epidural and around the incision. Within 6 days I moved from walker to cane and at two weeks I could have ditched the cane (doctor said to use it for 4 weeks to keep me from forgetting and taking off running!) except for the fact that my right hip very quickly became my "bad" hip. My new left one felt so darn strong! So at two weeks I switched the cane to support my unoperated hip when I walked for any distance. A week from tomorrow at 5 weeks post left hip, I will have a new right hip and the same leg length. I can hardly wait! So if you are looking for a quicker recovery with little, if any restrictions from day 1, I would seriously look at the anterior approach. While it sounds like the mini-posterieur has made advances in terms of incision size and the amount of muscles/tendons cut, there is still some cutting and that is the reason for the restrictions to prevent a dislocation until the muscles have healed. But as many have pointed out, the most important criteria is to have a surgeon who has done many surgeries with whatever approach it is they use because the surgeon's experience is to me the most important thing. @NewlyHip, don't mean to hijack your thread and I am so thrilled for you that your bilateral replacement is going so well!
cr8tvt
junior member
@CodeGirl, thanks -
my "patient's guide" from HSS didn't mention those differences. perhaps they have a different one for anterior replacements?
sounds like when the anterior goes well, it may be better, but my surgeon said that posterior gives better access to the site, and that when ligaments are too tight (worse for men than women) they may have to cut them anyway, and it is more difficult to repair them using the anterior approach. He seemed to think that with advances in the posterior approach, they are equally attractive. but i'll look a little further into the anterior approach.
and i'm clearly the one who hijacked @NewlyHip's thread - (;-))
can't tell you how much this has all helped -
this process is overwhelming at times, so to have people who have been through it take the time and show this much empathy to others they don't even know is truly inspiring -
this is clearly not the world you see on the nightly news -
thanks everybody -
psychteach
graduate
- Joined
- Dec 26, 2013
- Messages
- 730
- Age
- 62
- Location
- Palm Beach, Florida
- Gender
- Female
- Country
- United States
- Status
- Not open for further replies.





